






An unusually detailed and rare examination of an Alzheimer’s patient’s brain has provided researchers with a "smoking gun" in the long-standing debate over how to effectively treat the disease. By observing striking differences between regions of the brain where treatment successfully eradicated harmful amyloid plaques and areas where those plaques remained, scientists have gained significant insight into how these proteins interact to cause neurodegeneration.
The findings, presented at the 2026 Alzheimer’s Association International Conference and published in the journal JAMA, reveal that the regions cleared of amyloid showed little or no buildup of tau tangles—a secondary protein abnormality that is a primary driver of brain cell death and cognitive decline. Conversely, adjacent areas in the same brain that retained amyloid deposits exhibited significantly higher levels of tau and clear evidence of ongoing, progressive tissue damage.
This discovery serves as a rare, tangible piece of evidence from a human brain that the removal of amyloid plaques may act as a critical shield, protecting the brain from subsequent, more destructive processes associated with Alzheimer’s disease (AD). The results strongly suggest that the thorough and early clearance of amyloid could be the key to limiting tau accumulation and, by extension, slowing the clinical progression of the disease.
Understanding the Mechanism: The Amyloid-Tau Connection
To understand the magnitude of this discovery, one must look at the two primary culprits in Alzheimer’s pathology. For decades, the field has been dominated by the amyloid hypothesis, which posits that beta-amyloid—a protein that clumps together to form sticky plaques outside of neurons—is the foundational event in the disease cascade. As these plaques accumulate, they are believed to trigger a secondary, more devastating process: the formation of tau tangles.
Tau is a protein that normally stabilizes the internal structure of neurons. In the context of Alzheimer’s, it undergoes a chemical change that causes it to detach from its structural duties and form dense, toxic tangles inside the cells. While amyloid is often described as the "trigger," tau is widely considered the "executioner," as its accumulation correlates much more closely with the actual death of brain cells, the loss of memory, and the erosion of personality and cognitive function.
For years, researchers have hypothesized that amyloid buildup creates the biological environment necessary for tau to proliferate. However, proving this causal link in humans has been exceptionally difficult. While pharmaceutical companies have successfully developed anti-amyloid therapies—most notably lecanemab (Leqembi) and donanemab (Kisunla), which have received full FDA approval—the long-term impact of these drugs on tau in the human brain has remained a subject of intense scientific scrutiny.
A Unique "Goldilocks" Case Study
The study, conducted by researchers at the Perelman School of Medicine at the University of Pennsylvania, utilized a rare opportunity to examine brain tissue donated by a former clinical trial participant. The patient, who was in his fifties when diagnosed with mild cognitive impairment due to Alzheimer’s, participated in a trial for aducanumab—the first drug of its kind to receive accelerated approval, though it has since been withdrawn from the market.
The patient received 30 doses of the medication over a four-and-a-half-year period. Following his death approximately four years after his final dose—more than a decade after his initial symptoms first manifested—his brain was donated to the Center for Neurodegenerative Disease Research at Penn.
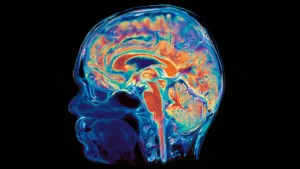
What the researchers discovered upon post-mortem examination was an extraordinary pattern of "patchwork" pathology. The brain exhibited a distinct, uneven distribution of amyloid clearance that acted as a natural experiment. The gyri—the raised, folding ridges on the surface of the brain—had been successfully cleared of most amyloid plaques. In these specific regions, there was a notable lack of tau tangles.
In contrast, the sulci—the deep grooves nestled between those ridges—still contained significant amyloid buildup. In these areas, the researchers observed high concentrations of tau, widespread inflammation, and clear signs of neurodegeneration. This uneven clearance pattern had been observed in scans taken while the patient was still alive, confirming that the drug’s efficacy varied significantly across different anatomical structures of the brain.
"Seeing both disease patterns side-by-side in the same brain gave us a rare opportunity to understand how amyloid removal affects other proteins that contribute to Alzheimer’s disease," said co-senior author David Wolk, MD, co-director of the Penn Memory Center and director of the Penn Alzheimer’s Disease Research Center. "The findings provide some of the clearest human evidence to date that anti-amyloid therapies may limit the accumulation of tau and slow the brain changes that lead to memory loss and cognitive decline."
Implications for Modern Alzheimer’s Treatment
The "Goldilocks" nature of this case, as described by co-senior author Edward B. Lee, MD, PhD, allowed the team to directly compare the progression of disease in neighboring regions under different biological conditions. Dr. Lee, who holds the John Q. Trojanowski, MD, PhD Professorship for Neurodegenerative Disease Research, emphasized that while many previous reports have shown either total clearance or limited clearance, this case provided a unique internal control that highlights the direct relationship between the removal of amyloid and the subsequent inhibition of tau.
This discovery has profound implications for the current generation of anti-amyloid monoclonal antibodies. These drugs, which work through mechanisms similar to the treatment the patient received, are designed to clear plaques to prevent the disease from worsening. If clearing amyloid can indeed "interrupt" the chain reaction that leads to tau accumulation, it justifies the aggressive pursuit of amyloid-clearing therapies, particularly when administered in the earliest stages of the disease.
However, researchers caution that this study, while groundbreaking, involves only one individual. It cannot yet establish a precise "threshold" for how much amyloid must be cleared to provide lasting clinical protection, nor can it definitively prove that the plaque clearance was the sole factor responsible for the localized differences in tau. Furthermore, the biology behind why some regions of the brain are more resistant to drug-mediated amyloid clearance than others remains an open question. Identifying why the drug was effective in the gyri but not in the sulci could be the key to developing the next generation of more potent, uniform therapies.
The Case for Early Intervention
The study also reinforces the growing consensus that timing is everything. Because amyloid proteins can accumulate in the brain silently for years—or even decades—before a patient experiences a single memory lapse, the window for effective intervention may be much earlier than previously thought.
"Patients may accumulate amyloid for years before symptoms appear," explained first author Christopher A. Brown, MD, PhD, an assistant professor of Neurology. "This case suggests that removing amyloid early may help limit the changes that ultimately damage brain cells. Ongoing trials will help determine whether starting treatment before symptoms begin can provide even greater benefit."
The medical community is currently shifting its focus toward identifying at-risk individuals during this "pre-clinical" phase. By targeting amyloid before the tau pathology becomes widespread and the neurodegeneration becomes irreversible, physicians hope to change the trajectory of the disease from an inevitable decline to a manageable, or perhaps even preventable, condition.
As clinical trials continue to evolve, the challenge remains in balancing the need for long-term data with the urgent necessity of providing treatments to patients today. Most clinical trials evaluate success over a period of 18 months, but the Penn study suggests that the true protective benefits of these drugs might only manifest over several years. This highlights a need for continued, long-term monitoring of patients who receive anti-amyloid therapies.
The findings from this study, supported by a significant series of grants from the National Institutes of Health, provide a vital piece of the puzzle. While there is still much to learn about the complex protein interactions that define Alzheimer’s, this rare glimpse into a single brain has provided a clear, compelling argument that the biological strategy of clearing amyloid is not just a theoretical goal, but a tangible path toward preserving brain health.